ABSTRACT
Nucleos(t)ide analogues (NA) are widely used to treat hepatitis B virus (HBV) infection, but they cannot eradicate the virus and treatment duration can be lifelong if the endpoint is set at seroclearance of the hepatitis B surface antigen (HBsAg). As an alternative strategy, finite NA therapy without the prerequisite of HBsAg seroclearance has been proposed to allow treatment cessation in patients with sustained undetectable HBV viremia for two to three years. However, reactivation of viral replication almost always follows NA withdrawal. Whereas HBV reactivation might facilitate HBsAg seroclearance in some, it could lead to serious acute flare-ups in a certain proportion of patients. Occurrence and consequences of NA withdrawal flares are complicated with various factors involving the virus, host, and treatment. Accurate risk prediction for severe flares following NA cessation is essential to ensure patient safety. The risks of life-threatening flares in patients who discontinued NA according to the stopping rules of current guidelines or local reimbursement policies have recently been quantitatively estimated in large-scale studies, which also provided empirical evidence to help identify vulnerable patients at risk of devastating outcomes. Moreover, risk predictors were further explored and validated to hopefully aid in patient selection and management. In this narrative review with a focus on patient safety, we summarize and discuss current literature on the incidence of severe flares following NA cessation, risk stratification for candidate selection, rules of posttreatment monitoring, and indications for treatment resumption. We also share our thoughts on the limitations of existing knowledge and suggestions for future research.
-
Keywords: Hepatitis B virus infection; Antiviral agents; Hepatitis B surface antigens; Patient safety
INTRODUCTION
Chronic hepatitis B virus (HBV) infection is the leading cause of liver-related morbidity and mortality, and remains a major threat to global public health, affecting 296 million people worldwide [
1]. Antiviral treatment using nucleos(t)ide analogues (NA) effectively inhibits viral replication, ameliorates hepatic necroinflammation, attenuates or reverses liver fibrosis, and reduces the risk of hepatocellular carcinoma (HCC) [
2-
4]. Current NA regimens include entecavir, tenofovir disoproxil fumarate (TDF), and tenofovir alafenamide (TAF), all of which possess high genetic barriers to the selection of resistance-associated variants and sustained viral suppression can be achieved in the vast majority of treated patients [
5]. Nevertheless, NA fails to eradicate HBV because their pharmacological activities are confined to the reverse transcriptase domain of the viral polymerase, without direct effects on the episomal covalently closed circular HBV DNA (cccDNA) and fragments of viral DNA integrated into the host genome, both of which can be transcriptionally active despite NA treatment [
6,
7]. NA withdrawal almost inevitably reactivates viral replication with potential clinical consequences [
8].
The optimal duration of NA treatment for chronic HBV infection has not been clearly defined and recommendations are inconsistent among current guidelines [
9-
11]. It is generally acceptable to stop NA after seroclearance of hepatitis B surface antigen (HBsAg), or the so-called functional cure, which signifies quiescence of replicational and transcriptional activities of the virus and predicts durable remission off NA treatment [
12]. Unfortunately, HBsAg seroclearance rarely occurs during ongoing NA treatment with an annual incidence rate below 1% [
13-
15]. This treatment endpoint is literally synonymous with indefinite treatment duration for most patients receiving NAs.
Indefinite NA treatment may have several theoretical disadvantages, including the challenge of maintaining medication adherence over an extended period [
16], the concern of long-term toxicity from prolonged drug exposure [
17], and the financial burden of sustained prescription costs [
18]. More importantly, it was found that the incidence of HBsAg seroclearance was paradoxically higher after NA discontinuation compared to during treatment [
14,
19], and a finite NA strategy of “stop to cure” was thus proposed [
20,
21]. The practice of stopping NA therapy without the requirement of HBsAg seroclearance is currently debatable with both perceived pros and cons (
Table 1). For patients who have initiated NA therapy with positive hepatitis B e antigen (HBeAg), current guidelines generally agree treatment cessation may be considered after achieving HBeAg seroconversion, followed by consolidation for one year or longer [
9-
11]. Contrary to HBsAg seroclearance, however, HBeAg seroconversion does not consistently predict sustained remission after NA cessation, even with additional consolidation for several more years [
22,
23]. The practice of finite NA therapy in patients with HBeAg-negative hepatitis B is highly debated with conflicting recommendations found in international and local guidelines (
Table 2) [
9-
11,
24-
30]. Such contradictory recommendations highlight the limitations of current knowledge on this issue. Central to the controversy is the concern about patient safety and most concerning is the risk of acute-on-chronic liver failure (ACLF), which is potentially fatal [
31].
Amid interests in and disputes over the finite approach of NA treatment for chronic HBV infection, there is a growing body of evidence reporting clinical outcomes following NA withdrawal [
32]. Knowledge about the safety of treatment cessation is indispensable to inform the practice of finite NA therapy, and data have been emerging to quantify the risk of severe withdrawal hepatitis flares and to identify the associated risk factors [
33-
35]. In this review with a special focus on patient safety, we summarized the data available to date and discussed the selection of patients suitable/unsuitable for NA cessation, patterns of off-therapy flares with implications for patient monitoring, and pragmatic considerations for the timing to resume antiviral therapy. We also stressed current knowledge gaps, pointed out pitfalls in existing literature, and provided our perspectives on future directions of research.
RISK OF SERIOUS ACUTE EVENTS ACCORDING TO CURRENT STOPPING RULES
Incidence of acute hepatitis flares following NA withdrawal
The risk of acute flare-up, a unique feature of chronic HBV infection that can abruptly develop without preceding symptoms and rapidly progress to liver failure within weeks [
36,
37], must be factored in the consideration of finite NA therapy. It is not surprising to observe acute hepatitis flares following NA withdrawal, because the sudden increase of viral replication along with surge in viremia is known to trigger host immunity against HBV [
38], as seen in the setting of immunosuppressive treatment without antiviral prophylaxis [
39,
40].
The incidence and “natural history” of HBV flares induced by NA withdrawal can be discerned in recent studies from Taiwan, where the reimbursement coverage for anti-HBV therapy is finite (usually three years of treatment) in principle, and patients need to withhold retreatment according to the strict criteria for treatment eligibility [
34]. In a large hospitalbased cohort study that applied the Asian Pacific Association for the Study of the Liver (APASL) criteria to select and monitor patients, Liu and colleagues found that acute flares (defined by elevation of serum alanine aminotransferase (ALT) ≥5 times the upper limit of normal [ULN]) occurred in 516 out of 1,234 patients (41.8%) within two years after treatment cessation, and reported that the corresponding cumulative incidence reached 42% [
35]. In a population-based study with a less selected patient population to represent real-world practice in Taiwan, Hsu and colleagues estimated the cumulative incidence of acute flares (ALT >200 U/L) was 30.7% (95% confidence internal [CI], 29.4–32.0%) at four years [
41].
Most but not all of the withdrawal flares can wane spontaneously or subside with NA retreatment. A severe episode may either present with or progress to ACLF that, in turn, could lead to mortality or the need of liver transplantation. Quantifying the risk of such a severe episode is hence important, but was found to be difficult in earlier studies with small samples and/or few events [
42]. This crucial gap in knowledge has recently been addressed by large cohort studies with more than 500 participants and also by pooled analyses of individual studies (
Table 3) [
33-
35,
43-
46]. In the Taiwanese population-based study by Hsu and colleagues, the cumulative incidence of severe flares with hepatic decompensation (defined by both hyperbilirubinemia and coagulopathy) was estimated at 1.8% (95% CI, 1.5–2.2%) at four years after treatment withdrawal [
41]. After pooling fifteen studies with 4,525 individual patients in a systematic review and meta-analysis of current literature updated to August 2022, Tseng and colleagues reported that 1.2% (95% CI, 0.70–2.1%) of patients would develop severe flares or hepatic decompensation (variably defined in respective studies) after stopping NA. The international RETRACT-B consortium also found that the cumulative incidence of hepatic decompensation (defined as hyperbilirubinemia, coagulopathy, or clinical complications) was 1.8% at five years [
33].
On the basis of these aforementioned studies, life-threatening flares were expected to occur in approximately 1–2% of HBV-infected patients who discontinued NA according to the stopping rules of earlier practice guidelines (mainly APASL) or local reimbursement policies. Notably, while the criteria of the APASL guidelines are the most stringent for treatment initiation [
9-
11], they are comparatively more liberal than those of the European Association for the Study of the Liver (EASL) and American Association for the Study of the Liver (AASLD) guidelines for stopping NA therapy (
Table 2).
Not all patients carry the same risk of withdrawal flares, and those at excessive risk of serious clinical outcomes should be advised against treatment cessation. It stands to reason that older patients and individuals with far advanced diseases are more vulnerable to devastating flares and this reasoning is now supported by empirical evidence. In a hospital-based study that followed the APASL guidelines to stop NA therapy, Jeng and colleagues [
14] found all seven patients who developed hepatic decompensation, and three patients who subsequently died, had liver cirrhosis. In larger studies that were statistically powered to explore risk predictors, liver cirrhosis was consistently identified as a risk factor significantly and strongly associated with serious clinical events following NA withdrawal [
35,
41]. It has also been shown that an older age was associated with excessive risk of severe withdrawal flares; more specifically, the risk significantly increased with age when the patients were 50 years or older [
41]. A higher risk was also observed in patients with a past history of hepatic decompensation or severe acute exacerbation [
41,
47].
SELECTION OF CANDIDATES FOR FINITE NA THERAPY
High retreatment rates without accurate patient selection
In addition to vulnerable patients at excessive risk of serious flares, individuals who are prone to relapses of clinical hepatitis and unlikely to clear HBsAg following treatment cessation are not suitable to practice finite NA therapy. Stopping NA in these patients bound to resume treatment only brings about unnecessary and potentially harmful interruption in viral inhibition and possible worsening of liver fibrosis. In fact, about half of the patients who stopped NA according to the rules recommended by earlier guidelines developed active hepatitis that fulfilled the usual criteria for antiviral therapy [
35,
41,
48,
49]. Such high retreatment rates reflect the insufficiency of current stopping rules to select candidates for finite NA therapy. On one hand, reactivation of viral replication following NA cessation often induces host immune responses that may facilitate seroclearance of HBsAg [
50,
51]. On the other hand, the elicited immune reaction could also result in severe necroinflammation with serious clinical consequences. It is currently unclear how this double-edged sword can be used to clear HBsAg without causing collateral damage [
52]. Notably, patients who developed clinical relapse (usually defined as serum ALT >2×ULNs in addition to HBV viremia >2,000 IU/mL) did not have a higher incidence of HBsAg seroclearance than those who remained clinically uneventful [
14]. Therefore, the practice of finite NA therapy requires prediction tools that can precisely identify patients at a lowest risk of clinical relapse and also a highest chance of HBsAg loss [
53].
A number of risk predictors, which can be grouped into virus, treatment, and host factors, have been reported to help distinguish patients at different risks of clinical relapse off NA therapy (
Fig. 1). Serum level of HBsAg at the end of therapy (EOT) is the most extensively studied and widely validated among them. It is useful to predict both the risk of hepatitis relapse and opportunity of HBsAg loss. In general, the lower the level of EOT HBsAg, the less risk of clinical relapse, and the higher chance of HBsAg seroclearance [
54-
57]. A cutoff point set at 100 IU/mL was proposed and later validated as the easily applicable threshold to select patients who may consider treatment cessation [
57,
58]. It should be noted, however, that the risk of clinical flares is lower but not negligible with an EOT HBsAg level <100 IU/mL. The risk can be further decreased by lowering the threshold, but clinical relapse may still occur with a EOT HBsAg level <40 IU/mL, as demonstrated in the study by Tseng and colleagues [
59]. Moreover, emerging data indicated that the EOT level of HBsAg did not predict severity of clinical relapse. Fatal flares could still occur in patients with a serum level of EOT HBsAg <10 IU/mL [
35].
Quantitation of hepatitis B core-related antigen (HBcrAg) in serum can be used to gauge transcriptional activity of the virus and may add to the accuracy of risk prediction based on HBsAg at EOT [
60,
61]. Hsu and colleagues demonstrated that both EOT levels of HBsAg and HBcrAg were both independent risk factors associated with clinical relapse off NA therapy although these two biomarkers were positively correlated with each other [
62]. Nevertheless, how to apply HBcrAg on top of HBsAg in the process of decision making to select candidates for NA cessation remains to be defined. In patients with a low EOT HBsAg (e.g., below 100 or 200 IU/mL), the level of HBcrAg at EOT was found unable to further stratify their relapse risks [
59,
63,
64]. On the other hand, encouraging results were reported in studies that simultaneously combined the two biomarkers together instead of placing one after the other in successive steps [
45,
62,
65,
66].
Other HBV biomarkers that have been reported to predict responses off NA therapy include serum viral load and HBeAg status at treatment initiation [
67,
68], titer of serum HBV RNA at EOT [
64], HBV genotypes [
55,
59,
69], and diversity of viral quasispecies [
70]. A lower serum HBV DNA (e.g., <200,000 IU/mL) and negative HBeAg status at the start of antiviral therapy were associated with a lower risk of off-NA relapse [
67,
68]. In patients with a low EOT HBsAg (e.g., <200 IU/mL), detectable HBV RNA in serum were found to foretell a higher rate of virological relapse [
64]. In addition, HBV genotype C versus genotype B was linked to a greater chance of HBsAg loss in Asian patients although the association with off-NA relapse was inconsistent across studies [
55,
59,
69]. A higher pretreatment HBV quasispecies diversity was also found to predict sustained virological response (HBV DNA <2,000 IU/mL) for more than one year off therapy [
70].
Host factors that are reportedly associated with relapse or remission off NA include age, genetic polymorphisms, ethnicity, circulatory biomarkers of inflammation or immunity, and HBV-specific immune response. As seen in the association with serious life-threatening flares, an older age has been shown to be a significant risk factor for relapses of clinical hepatitis overall [
54,
55,
68]. A pilot study by Su and colleagues [
71] found that polymorphisms of CTLA4 and HLA-DPA1, both of which were genes involved in regulation of immune reactions, were predictive of off-NA relapse and clinical response, respectively. There were also preliminary data suggesting that circulatory biomarkers of immunity, such as titers of hepatitis B core antibody (anti-HBc) [
72,
73] and RNA levels of
IFNγ,
IL-8,
FASLG, and
CCL4 genes from peripheral blood mononuclear cells [
74], could help identify patients who would suffer relapses off NA treatment. In fact, a biomarker of hepatic necroinflammation readily available in routine clinical care, i.e., the serum level of ALT, may also add to the risk prediction of off NA relapse [
54]. The chance of HBsAg seroclearance was also significantly higher in Caucasian patients than in Asian patients although the incidence of ALT flares did not appear to differ by ethnicity [
33,
48,
75]. This association might reflect differences in the geographic distribution of HBV genotypes, because the genotype was predominantly A or D in Caucasians, but B or C in Asians [
75,
76]. The mode of transmission, the age/duration of infection, or host genetic polymorphism should also be considered. Further research is warranted.
Adaptive immune responses are essential in clearing or controlling HBV infection, and also crucial in mediating liver injury that drives disease progression in patients with CHB [
77-
79]. The importance of HBV-specific immune response in the prediction of off-NA outcomes has recently been demonstrated. Rivino et al. [
80] reported that presence of HBV core and polymerase-specific T cells during NA therapy was associated with absence of flares off treatment. Comparably, increased frequency of functional HBV-specific CD8+ T cells at treatment withdrawal was associated with HBsAg loss or viral control in the study by García-López et al. [
81] Rinker and colleagues also showed that the exhaustion of T cells, which is characteristic of CHB [
82], was less severe in patients who cleared HBsAg after stopping NA [
51].
Nevertheless, whether NA withdrawal may enhance HBV-specific T-cell immune response is unclear in view of limited and conflicting data [
51,
81]. Moreover, the probability of functional HBV-specific CD8+ T cell response on NA treatment was found to be significantly correlated with the duration of treatment and EOT HBsAg, both of which were also significant factors associated with off-NA outcomes [
83]. Therefore, more research is needed to clarify how HBV-specific immune responses may be factored into the consideration of NA withdrawal.
Treatment-related factors that may impact the risk of off NA relapses include the duration of treatment and the regimen that is discontinued. Earlier studies have shown that a short duration (<6 months) of on-therapy HBV DNA undetectability is predictive of off-therapy relapse [
84]. A large body of evidence corroborates an important role for the duration of treatment consolidation, which is defined by the period following HBeAg seroconversion in HBeAg-positive patients, or that after serum HBV DNA becomes undetectable in patients with HBeAg-negative hepatitis B, to determine the risk of off-NA relapse [
85-
87]. In general, a minimum of one year is required for NA consolidation and extension for two or three years may be preferred [
85-
87]. Whether further extension beyond three years confers additional benefits to protect against off-therapy relapses has not been confirmed by empirical evidence. Moreover, the types of NA therapy can impact the relapse patterns. Off-treatment relapse occurred significantly more slowly and less frequently with ETV as compared with other regimens including TDF [
68,
71,
86,
88,
89].
With a few risk predictors uncovered and none sufficiently accurate by themselves, it follows that several independent risk factors may be considered together to improve the precision of risk stratification. The Japan Society of Hepatology (JSH) is the first to endorse application of a scoring formula to select candidates for treatment cessation (
Table 2). The JSH score was based on serum levels of HBsAg (<80 IU/mL, 80–800 IU/mL, and ≥800 IU/mL scored 0, 1, and 2 points, respectively) and HBcrAg (<3 log IU/mL, 3–4 log IU/mL, and ≥4 log IU/mL scored 0, 1, and 2 points, respectively) at EOT [
90]. A total score of 3 or 4 points indicated a high risk of relapse and argued against cessation. Regrettably, external validation of the JSH score has been limited.
The SCAEL-B score is another attempt to integrate information collected at EOT to stratify the risk of clinical relapse [
62]. The scoring formula: 35*HBsAg (log IU/mL)+20*HBcrAg (log U/mL)+2*age (year)+ALT (U/L)+40 for tenofovir use (as compared with ETV) consisted of five variables that were conveniently applicable in daily practice. A total score ≥320 points indicates a high risk of relapse and low chance of HBsAg seroclearance, while a score <260 points predicts the opposite. The SCALE-B score outperformed the JSH score in the development study and has been independently examined in different patient cohorts with conformed validity in most, albeit not all, of the studies (
Table 4) [
45,
65,
66,
91]. Nevertheless, it has not been validated in a prospective setting so far, nor has it been calibrated, and appeared insufficient to predict HBsAg seroclearance.
PATIENT MONITORING AFTER TREATMENT CESSATION
Time patterns of off-therapy flares according to NA agents
Close monitoring after treatment is essential to detect HBV reactivation early and effectively manage acute flares, which can insidiously develop but rapidly deteriorate. How close the monitoring should be, however, is unknown [
92]. To date, no monitoring program has been prospectively validated to guarantee patient safety. There is only anecdotal and indirect evidence to support current recommendations for posttreatment monitoring.
Generally speaking, NA withdrawal may quickly reactivate HBV replication and usually result in virological relapses within three months after treatment cessation. This timing of off-therapy relapses applies to most NA agents other than ETV [
67,
68,
71,
88,
89]. For TAF, data is currently limited but it appeared similar to TDF in a pilot study [
93]. Therefore, a monthly checkup of serum HBV DNA and ALT is advisable during the first three months. If viremia substantially rebounds and/or ALT flares take place, the management should be individualized with no scheme that can fit all. In principle, subsequent monitoring should be more intense (e.g., every one to two weeks) especially when retreatment was withheld. For patients who do not discontinue ETV and do not encounter virological and/or clinical relapses in the first three months, the follow-up intensity might be decreased to every two to three months through the first year off treatment [
92].
ETV is unique for a late timing of off-treatment relapses [
67,
71], of which the mechanism remains enigmatic. It is common for ETV stoppers to run into virological or clinical relapses after the first three months [
8]. Therefore, the monitoring intensity for ETV stoppers may be increased to monthly or bimonthly from the first three months onward until at least one year after treatment cessation.
Although the majority of relapses take place within one year following NA withdrawal, they can still occur years afterwards [
34,
35]. As a matter of fact, it is possible for patients to suffer HBV reactivation with resultant acute hepatitis flares as long as the viral replication remains active. Disease awareness cannot be overemphasized for NA stoppers, particular those patients with positive indicators for a vigorous viral activity, such as substantial HBV viremia >2,000 IU/mL or high titers of HBsAg >1,000 IU/mL. Patients should be educated to recognize symptoms and signs suggestive of acute flares and instructed to seek medical attention as soon as possible whenever they notice or suspect the manifestations of hepatic insufficiency. Besides the due concern over acute flares and resultant complications, attention should be paid as well to more stealthy progression of the disease, such as worsening of liver fibrosis and development of HCC.
Posttreatment monitoring can be opportunely informed by changes in time-varying factors that foretell an upcoming bout of acute HBV flare-up. Exploration of dynamic risk predictors for posttreatment monitoring, however, has attracted far less research effort as compared to static factors at treatment initiation or EOT. Although empirical data are relatively sparse, it is conceivable that serum levels of viral DNA and HBsAg, the two convenient biomarkers that have been useful in many aspects of clinical care of HBV infection, can also be used in this application. Serum HBV DNA measured at one month after NA cessation was found to disclose early signals of imminent relapses [
71]. The investigators found that one log higher in serum HBV DNA was independent of age, biological sex, NA regimen, and EOT HBsAg level to confer a 50% (hazard ratio [HR], 1.5; 95% CI, 1.1–2.0) increase in the risk of forthcoming clinical relapse. A similar finding was reported in a recent study, which found a significant association between serum HBV DNA at week 6 off-therapy and ALT flares (ALT >5× ULN) with a HR of 1.2 (95% CI, 1.0–1.8). HBV viremia >10,000 IU/mL at week 6 was estimated to confer roughly a 3.5-fold higher risk of withdrawal flares (HR, 3.4; 95% CI, 1.4–8.4) [
94]. In addition to the viral load measured at fixed time points, that of virological relapse was found to predict subsequent clinical relapse and also severe flares which required retreatment. It was shown that 89.7% (95% CI, 72.4–98.2%) of the patients with a viral load >100,000 IU/mL at the virological relapse developed clinical relapse, and 88.0% (95% CI, 68.7–97.9%) of them would need to resume treatment in two years [
95].
How fast serum HBV DNA rises may also affect the risk of off-therapy flares. A recent retrospective study reported that a much steeper HBV DNA upsurge was associated with the risk of severe flares although the association appeared to interact with the NA regimen [
96].
Serum level of HBsAg may markedly change following NA withdrawal in contrast to the typically unfluctuating state during continuous treatment. The time-varying HBsAg level in posttreatment follow-up can be useful to stratify the risk of subsequent relapses. Chien and colleagues [
97] confirmed that the dynamic levels of serum HBsAg was associated with forthcoming virological and clinical relapses in a prospective cohort study with serum HBsAg measured every three months after treatment cessation. They reported that the risk of subsequent clinical relapse was very low (only one in nineteen patients) with a HBsAg level below 10 IU/mL.
CONSIDERATIONS OF THE CRITERIA TO RESTART ANTIVIRAL THERAPY
Dilemma over the timing of treatment resumption
It is currently unknown and highly contentious when to resume antiviral treatment in NA stoppers who wish to give finite therapy a try. On one hand, retreatment cannot be withheld until the manifestations of jaundice or coagulopathy, let alone full-blown complications of ACLF. When acute HBV flare manifests with hepatic decompensation, it is not always rescuable by antiviral treatment and may necessitate a timely liver transplant to save lives. Even if the episode is not fatal on the spot, it may leave consequences in the long run as substantial hepatic necrosis is known to accelerate liver fibrosis toward cirrhosis with an increased risk of HCC [
98]. Therefore, immediately restarting antiviral therapy for withdrawal flares with the manifestations of liver insufficiency is certainly indicated, but is already too late to ensure patient safety.
On the other hand, recurrent viremia of itself is not an ideal indication for treatment resumption, because it is nearly universal following NA cessation. If patients want to restart treatment due to reappearance of HBV DNA in serum, they should not have interrupted the therapy in the first place. Nevertheless, it is debatable whether retreatment is indicated for recurrence of viremia with serum HBV DNA rising to a certain level with clinical implications. For instance, a viral load >2,000 IU/mL can be considered to be clinically significant and may arguably indicate antiviral therapy [
99-
101]. Regrettably, virological relapse is still very common in patients who stop treatment as per the criteria of current guidelines although it is not inevitable for carefully selected candidates, such as those with a low HBsAg and/or HBcrAg at EOT [
8,
54,
64]. If virological relapse is fiercer with a higher viral load (e.g., >100,000 IU/mL or higher), patients may consider restarting antiviral therapy, whether or not the episode is accompanied by substantial elevation of serum ALT. Withholding retreatment may not be necessary, because a fierce rebound of viremia often forecasts clinical flares that eventually require antiviral therapy [
94-
96].
Rise of serum ALT may constitute the indication for retreatment following NA cessation. Various criteria have been proposed in different institutions and studies (
Table 5) [
34,
64,
102-
108]. Modest elevation of serum ALT (generally 1–5×ULN) in the absence of hepatic insufficiency was usually managed with close monitoring and retreatment was withheld for a certain period of time (generally one to three months). It has long been observed that serum ALT frequently fluctuated after NA withdrawal, but often could subside without retreatment [
19].
Another major reason to withhold retreatment is the belief that restarting antiviral therapy may lower the chance of HBsAg seroclearance. The incidence of HBsAg seroclearance was shown to be significantly higher in patients who experienced clinical relapse and remained untreated than in those clinical relapsers who were retreated [
67]. While this observation may encourage NA stoppers who are eager to clear HBsAg not to restart therapy as soon as facing mild fluctuations in serum ALT, it warrants noticing that the timing of retreatment was not randomly assigned in any study conducted to date. Whether the association is causal or confounded remains unclear, particularly when the status of exposure (i.e., clinical relapse or not, retreatment or not) is determined by events that occur after the inception of observation. Moreover, it is not clear how late is too late to avert deterioration to hepatic decompensation. Therefore, patients should not be discouraged from resuming treatment for clinical relapse, which actually meets the usual indication for treatment initiation [
9-
11]. For sufficiently informed patients who wish to watch and wait, intensive follow-up (every one to two weeks) is strongly advised.
In our opinion, a significant increase in serum ALT (e.g., >10 times ULN) requires immediate retreatment to reduce the risk of further progression, as acute HBV flares cannot always be predictable and the harm of delaying treatment has been well documented [
109,
110]. On the assumption that treating “good” flares would hinder HBsAg seroclearance, some experts have suggested withholding treatment for withdrawal flares and using the kinetics of serum HBsAg and ALT levels to guide retreatment [
111,
112]. However, data on the HBV-specific T cell immune response to support the practice of withholding treatment for “good” withdrawal flares is not available. In fact, existing data indicating an increase in HBV-specific adaptive immune response was not associated with withdrawal flares [
80,
81]. The speculation that retreatment would hinder immune reactions was based on anecdotal evidence from observational research [
14,
112]. Moreover, how reliably HBsAg and ALT kinetics can distinguish “good” from “bad” flares has not been prospectively attested. For the benefit of patient safety, we maintain that any proposed rule for withholding treatment in the event of acute HBV flares should be thoroughly scrutinized and validated in prospective studies before being adopted in clinical practice. After all, the consequence of an inaccurate prediction can be irreversible.
LIMITATIONS IN CURRENT KNOWLEDGE AND PERSPECTIVES FOR FUTURE RESEARCH
Interpretation of current literature to evaluate safety of NA cessation requires great caution. First of all, safety outcomes were not adequately reported and could be severely underestimated in existing studies [
42]. Serious adverse events were often not specified as a study endpoint and might not have been mentioned at all. In those studies that included severe hepatitis flares or hepatic decompensation, one third (14 out of 46 reports) did not clearly define the safety events [
43]. In fact, most of the previous studies focused on virological or clinical relapse and the observation could have been censored before occurrence of a more serious event [
32,
42]. Accordingly, we believe it is mandatory to include safety events as one of the study endpoints in every research that reports patient outcomes following NA cessation. Such events should be prespecified with a clear definition to allow for validation of the research, comparison among studies, and pooled analysis of relevant data. In addition, much of the available data originates from select specialist centers and ethnic groups and may not be representative of the entire population with CHB, especially those patients who receive care at primary care settings.
Moreover, existing studies were mostly retrospective and highly heterogeneous in various aspects, including compositions of patient populations, eligibility criteria for NA cessation, posttreatment monitoring, indications for retreatment, and measurements of outcomes [
32,
43,
87]. For instance, the proportion of patients with cirrhosis and the criteria for retreatment varied greatly among studies. Without great caution, knowledge synthesis from the literature could be inaccurate and study findings would be erroneously extrapolated to patients who were not represented in the study [
42,
113]. In particular, there was a substantial heterogeneity in definitions. What defined a “severe” flare differed across studies. It could be a marked elevation of serum ALT alone, ALT elevation accompanied with jaundice, ALT elevation with both jaundice and coagulopathy, or overt complications of ACLF. Different definitions certainly lead to different estimates of a “nominally same” event [
114]. In order to avoid confusion and thus facilitate advancement of the knowledge, we advocate for an international consensus among leading groups or experts in the field to unify the definitions that are crucial in the studies of NA cessation.
Existing evidence so far has not confirmed the superiority of finite NA therapy over continuous treatment in improving patient outcomes. There should be tangible benefits with measurable effects to justify the risk of potential consequences following HBV reactivation in patients who electively stop the medication. Ideally, the safety, efficacy, and effect size (if effective) of a treatment strategy as compared to the standard of care needs to be evaluated by data from randomized controlled trials that are statistically powered with a representative patient population. Regrettably, evaluation of finite NA therapy is currently based predominantly on observational studies, in which the decision to stop or continue NA treatment was easily confounded. Only three randomized trials were reported to date and one of them has not been fully published. Notably, the results were inconsistent for the effect on HBsAg seroclearance (
Table 6) [
102-
104]. Further evidence from robust randomized controlled trials is required for this treatment strategy to be considered standard care [
115,
116]. After all, what was approved by regulatory agencies to treat HBV was administration of NA instead of withdrawal from it [
117]. Certainly, such a trial must be carefully planned and meticulously executed with patient safety considered as first priority.
Despite recent progress, current knowledge is insufficient for an accurate prediction of clinical outcomes in most NA stoppers. Many of the reported risk predictors have not been externally validated by data from independent study populations and thus, their generalizability is uncertain. How to accurately predict the consequences of ALT flares is particularly crucial but largely unknown. In view of the potential rapidity from ALT elevation to hepatic insufficiency [
117], the risk of ACLF cannot be negligible unless “good” and “bad” flares can be reliably predicted before the flares. Elevation of serum ALT is already a sign of liver injury. The development of biomarkers to forecast outcomes of HBV reactivation requires deeper understanding of immune responses and resultant tissue injuries that underlie different clinical phenotypes [
79]. Regrettably, data about HBV-specific immune responses to NA withdrawal are very limited to date. Inclusion of immunological factors into the prediction models, which currently are based on viral antigens [
27,
62,
75], could further improve the predictive accuracy. To this end, we believe dynamic monitoring of both viral factors (activities of replication and/or transcription) and host factors (especially adaptive immune responses) during posttreatment follow-up could be helpful and worthy of study.
CONCLUSIONS
Discontinuation of NA therapy leads to HBV reactivation in most of the patients who discontinued NA per the criteria recommended in guidelines. Virological and clinical relapses were common, but seroclearance of HBsAg only occurred in a minority of patients. Moreover, approximately 1% of the NA stoppers suffered severe withdrawal flares with hepatic decompensation. Accurate risk prediction is essential to identify the candidate who can safely stop NA. A useful tool is likely to include viral, host, and therapeutic factors. Close follow-up after NA cessation is mandatory, but how close the monitoring should be is not yet clear. A posttreatment surge in serum HBV DNA with a high-level viremia forecasts clinical events and may be considered an indication to restart antiviral therapy. Withholding retreatment on ALT flares cannot be recommended as a routine practice, because rapid deterioration is not always predictable and potentially devastating. In the interest of patient safety, elective discontinuation of NA therapy can only be considered in carefully selected, highly motivated, and fully informed individuals who consent to the uncertainties during posttreatment monitoring (
Fig. 2).
ACKNOWLEDGMENTS
The manuscript has been edited by Marc Anthony for structure, flow, and language usage. This article is supported by a research grant from the Tomorrow Medical Foundation (funded to Yao-Chun Hsu).
FOOTNOTES
-
Authors’ contribution
All authors had access to the reviewed data and participated in the drafting, editing, and final approval of the manuscript for publication.
-
Conflicts of Interest
Yao-Chun Hsu has received research grants from and served as an advisory committee member for Gilead Sciences, and received lecture fees from Abbvie, Bristol-Myers Squibb, Gilead Sciences, Merck Sharp & Dohme, and Novartis, outside the submitted work. Cheng-Hao Tseng has received lecture fees from Abbvie, Bristol-Myers Squibb, Gilead Sciences, Merck Sharp & Dohme, Roche, and Bayer, outside the submitted work. Jia-Horng Kao has served as a consultant for Abbvie, Gilead Sciences, Merck Sharp and Dohme, and Roche and on speaker’s bureaus for Abbvie, Bristol-Myers Squibb, Gilead Sciences, Merck Sharp and Dohme.
Figure 1.Host, virus, and treatment factors associated with clinical relapse after cessation of nucleos(t)ide analogues. ALT, alanine aminotransferase; DNA, deoxyribonucleic acid; EOT, end of treatment; ETV, entecavir; HBcAb, anti-hepatitis B core-antibody; HBcrAg, hepatitis B core-related antigen; HBeAg, hepatitis B e-antigen; HBsAg, hepatitis B s-antigen; HBV, hepatitis B virus; RNA, ribonucleic acid; NA, nucleos(t)ide analogue; TDF, tenofovir disoproxil fumarate.

Figure 2.Safety considerations along the proposed scheme for an elective cessation of nucleos(t)ide analogues. ALT, alanine aminotransferase; DNA, DNA, deoxyribonucleic acid; EOT, end of treatment; ETV, entecavir; HBeAg, hepatitis B e antigen; HBsAg, hepatitis B surface antigen; HBV, hepatitis B virus; NA, nucelos(t)ide analogue; RNA, ribonucleic acid; TDF, tenofovir disoproxil fumarate; ULN, upper limit of normal.
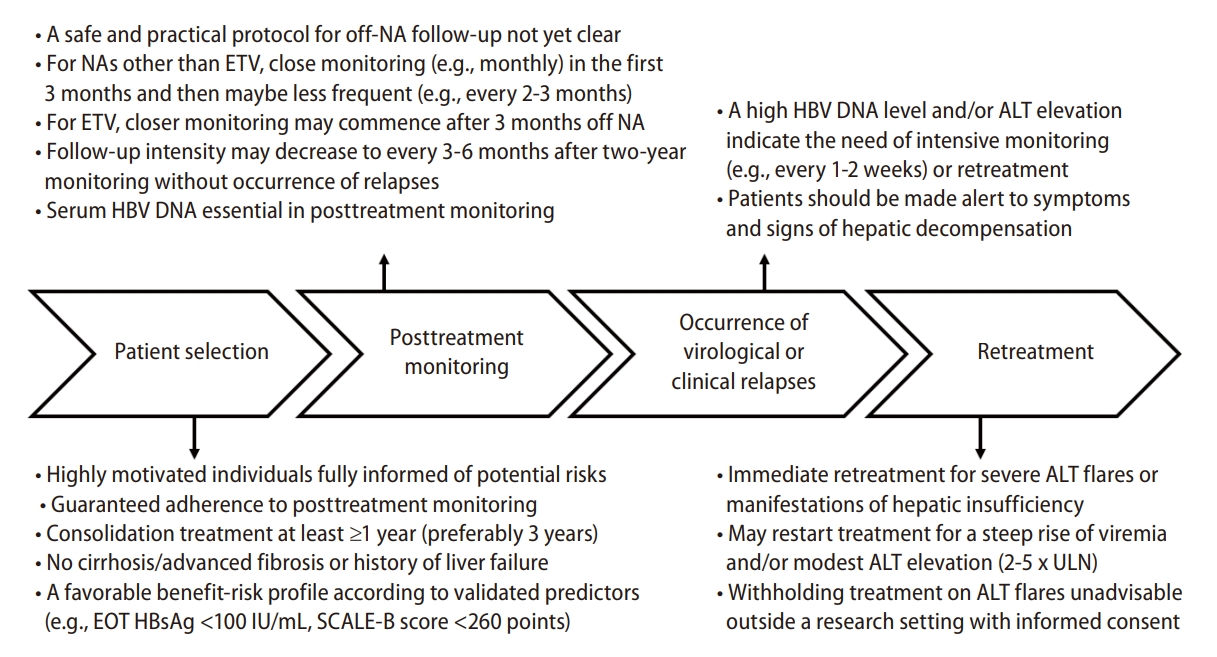
Table 1.Presumed pros and cons of the finite nucleos(t)ide analogue therapy for chronic hepatitis B virus infection
Table 1.
|
Pros |
Cons |
|
√ Triggering virus-specific immune reactions to control the infection |
· The provoked necroinflammation can be fulminant or unremittent |
|
√ The chance of HBsAg seroclearance is higher compared to continuous therapy |
· The risk of acute hepatitis flare is not always predictable and potentially fatal |
|
√ Addressing the difficulty of adherence to long-term medication |
· Close follow-up and easy access to healthcare may not be guaranteed |
|
√ Easing the financial burden incurred by drug prescription |
· Adding expenses on posttreatment monitoring and managing flares |
|
√ Relieving the concern of uncertain toxicity from prolonged drug use |
· Arousing anxiety about the uncertainty of HBV reactivation |
Table 2.Current guidelines for the criteria of stopping NA in patients with HBeAg-negative hepatitis B
*
Table 2.
|
Guideline |
Non-cirrhosis |
Cirrhosis |
|
International guidelines |
|
AASLD [9] |
· Indefinite treatment duration (Quality and Certainty of Evidence: Low Strength of Recommendation: Conditional) |
· Treatment discontinuation not recommended |
|
· May be considered in patients with HBsAg loss, but evidence insufficient |
|
APASL [10] |
· HBsAg loss following either anti-HBsAb seroconversion or at least 12 months of a post-HBsAg clearance consolidation period (B1), or |
· May be considered with a careful off-therapy monitoring plan (A1) |
|
· Treatment for ≥2 years with consolidation ≥1 year (B1) |
|
EASL [11] |
· HBsAg loss, with or without anti-HBsAb seroconversion (Evidence level II-2, grade of recommendation 1), or |
· Treatment discontinuation not recommended |
|
· May be considered after consolidation ≥3 years if close monitoring can be guaranteed (Evidence level II-2, grade of recommendation 2). |
|
WHO [24] |
· Life-long therapy in general |
· Treatment discontinuation not recommended |
|
· Discontinuation may be considered exceptionally in persons who can be followed carefully long term for reactivation and with persistently normal ALT levels and persistently undetectable HBV DNA levels |
|
· May be considered in persons who have evidence of persistent HBsAg loss and after completion of at least one additional year of treatment, regardless of prior HBeAg status. |
|
National guidelines |
|
Canada [25] |
· HBsAg loss (moderate recommendation; class 2, level B) |
· HBsAg loss or indefinite duration (moderate recommendation; class 2, level B) |
|
China [26] |
· The therapy aims are “clinical cure” (i.e., functional cure) |
|
|
· No recommended criteria for stopping treatment |
|
· No specific recommendations for patients with cirrhosis |
|
Japan [27] |
· In general, it is necessary not to stop administration of the NAs |
· Long-term treatment (Level 5, Grade B) |
|
· HBsAg loss (can be considered) |
|
· Treatment for ≥2 years without detectable HBV DNA or high relapse risk score according to serum HBcrAg and HBsAg levels |
|
Korea [28] |
· HBsAg loss (A1). |
· Long-term treatment (B1) |
|
· With reference to HBsAg level, cessation of NA therapy could be considered (B1). |
|
· HBcrAg and HBV RNA can be performed when considering cessation of NA therapy (B2) |
|
Sweden [29] |
· HBsAg loss (B1) |
· Long-term treatment (A1) |
|
· May be considered after long-standing treatment response but require close monitoring after termination(B2) |
|
Turkey [30] |
· HBsAg loss |
· Long-term treatment |
Table 3.Summary of large-scale studies (>500 participants) and meta-analyses on the risk of severe withdrawal flares with hepatic decompensation or liver failure
Table 3.
Cohort studies
|
|
Author (year) |
Study type/Region |
Number |
Age |
Pretreatment status
|
Criteria
|
Severe adverse events
|
|
Cirrhosis |
HBeAg(+) |
Stopping NA |
Resuming NA |
Severe hepatitis flares or decompensation§
|
Death or liver transplantation |
Risk factors |
|
RETRACT-B Hirode et al. [33] (2023) |
Prospective/International |
1,557 |
52.9†
|
11.8% |
15.8% |
As pre institution |
As per institution |
20 (1.3%) |
4 (0.3%)∥
|
· iCirrhosis |
|
Year
|
Incidence
|
95%CI
|
|
· iPretreatment HBeAg(+) |
|
1 |
1.0% |
0.6–1.6% |
|
|
2 |
1.4% |
0.9–2.2% |
|
|
3 |
1.6% |
1.1–2.5% |
|
|
4 |
1.8% |
1.1–3.0% |
|
|
5 |
1.8% |
1.1–2.0% |
|
|
Hsu et al. [34] (2022)*
|
EHR/Taiwan |
665 |
50.3‡
|
14.3% |
26.0% |
Taiwan reimbursement |
Taiwan reimbursement |
24 (3.6%) |
2 (0.3%) |
· iCirrhosis |
|
i· Male |
|
Liu et al. [35] (2022) |
Prospective/Taiwan |
1,234 |
56.4†
|
40.1% |
0% |
APASL 2012 |
Taiwan reimbursement |
Hepatitis flares: 516 (41.8%) |
5 (0.4%) |
· iCirrhosis · iPrior-treatment |
|
Decompensation: 13 (1.1%) |
· iAge (cut-off: 55) · iGenotype B |
|
· iTDF (vs. ETV) |
|
· iPretreatment viral load (cut-off: 6 log IU/mL) |
|
· iPretreatment-HBsAg (cut-off: 3 log IU/mL) |
|
· iEOT-HBsAg (≥500 vs. <100 log IU/mL) |
|
PS: the predictors for hepatitis flares, not for decompensation |
|
Hsu et al. [41] (2021) |
EHR/Taiwan |
10,192 |
50.9†
|
10.7% |
n.a. |
Taiwan reimbursement |
Taiwan reimbursement |
132 (1.3%) |
51 (0.5%) |
· iCirrhosis |
|
4 year: 1.8% (95% CI, 1.5–2.2%) |
4 years: 0.7% (95% CI, 0.5–1.9%) |
· iMale |
|
· iAge (cutoff age, 50 years) |
|
· iHistory of liver failure |
|
Ma et al. [44] (2019) |
Prospective and retrospective/Taiwan |
535 |
50.7†
|
0% |
29.9% |
APASL 2012 |
Taiwan reimbursement |
7 (1.3%) |
1 (0.2%) |
n.a. |
|
CREATE Sonneveld et al. [45] (2022) |
Prospective and retrospective/International |
572 |
52.0‡
|
n.a. |
16.6% |
As per institution |
As per institution |
2 (0.4%) |
0 (0%) |
n.a. |
|
Wong et al. [46] (2020) |
EHR/Hong Kong |
1,076 |
59.1†
|
8.3% |
0% |
n.a. |
n.a. |
7 (0.7%) |
n.a. |
n.a. |
Meta-analysis study
|
|
Author (year)
|
Enrolled studies
|
Main finding
|
|
Tseng et al. [43] (2022) |
50 articles reporting safety outcomes after NA cessation |
· Heterogeneous design among studies (e.g., stopping rules, retreatment criteria, and definition of decompensation) |
|
15 studies (4,525 patients) pooled for risk estimate of overall population |
· Serious adverse events not often reported in smaller studies with shorter follow up duration |
|
14 studies (3,731 patients) pooled for risk estimate of non-cirrhotic population |
· Risk estimate (95% CI): |
|
5 studies (744 patients) pooled for risk estimate of cirrhotic population |
|
Overall
|
Non-cirrhosis
|
Cirrhosis
|
|
Severe |
1.2% |
0.9% |
3.6% |
|
flares/Decompensation |
(0.7–2.1%) |
(0.4–1.8%) |
(1.8–7.3%) |
|
Death/Liver |
0.4% |
0.3% |
1.0% |
|
transplantation |
(0.2–0.7%) |
(0.1–0.7%) |
(0.5–2.1%) |
Table 4.Original study developing the SCALE-B score and external validation studies in independent patient populations
Table 4.
|
Author (year) |
Race/Region/Setting |
Number |
Age (year) |
Male (%) |
Pre-treatment HBeAg (+) |
ETV/TDF proportion |
Cirrhosis |
Stopping rule |
Duration (month): Treatment/Consolidation/Follow-up |
Event: Clinical relapse/HBsAg loss |
Performance of the SCALE-B
|
|
Clinical relapse |
HBsAg loss |
|
Hsu et al. [62] (2019) |
Asian/Taiwan/Prospective Multicenter |
135 |
49.5*
|
80.7 |
31 (22.9%) |
100% |
0% |
Treatment duration ≥3 years with undetectable HBV DNA and negative HBeAg on treatment cessation |
36.7*/25.2*/25.9*
|
66 (48.9%)∥/8 (5.9%) |
AUC**: |
3-year incidence**
|
|
1Y: 0.87 (0.80–0.93) |
High risk: 0 |
|
3Y: 0.87 (0.79–0.94) |
Intermediate: 0 |
|
5Y: 0.90 (0.79–1.00) |
Low risk: 27.1% (14.5–47.3%) |
|
5-year cumulative |
|
incidence**
|
|
High risk: 86.2% (67.8–96.8%) |
|
Intermediate: 61.6% (48.2–75.2%) |
|
Low risk: 17.2% (7.5–36.9%) |
|
CREATE Sonneveld et al. [45] (2022) |
Mixed (Asian:79.9%)/ International/Prospective and retrospective |
572 |
52*
|
68.2 |
16.6% |
77.8% |
n.a. |
Per institution |
73.8*/n.a./12§
|
92 (16.1%)‡/24 (4.2%) |
Proportion at week 48§
|
Proportion at week 48§
|
|
High risk: 31% |
High risk: 1% |
|
Intermediate: 14% |
Intermediat: 2% |
|
Low risk: 3% |
Low risk: 11% |
|
Liao et al. [65] (2021) |
Asian/China/Prospective Single center |
122 |
34*
|
77.9 |
100% |
58.2% |
0% |
APASL 2012 |
56.4*/30.0*/36.0*
|
44 (36.1%)∥/12 (9.8%) |
AUC**
|
Not mentioned |
|
1Y: 0.81 (0.73–0.89) |
|
3Y: 0.74 (0.65–0.84) |
|
5Y: 0.75 (0.65–0.85) |
|
5-year cumulative |
|
incidence**
|
|
High risk: 82.2% |
|
Intermediat: 50.0% |
|
Low risk:22.2% |
|
Papatheodoridis et al. [66] (2020) |
Caucasian/Greece/Prospective Multicenter |
57 |
60*,†
|
64.9 |
0% |
100% |
0% |
Treatment duration ≥4 years, ETV or TDF ≥2 years, and undetectable HBV DNA ≥3 years |
n.a./63.6*/19.0*
|
19 (33.3%)∥/12 (21.1%) |
No association |
Not mentioned |
|
Kaewdech et al. [91] (2022) |
Asian/Thailand/Prospective Single center |
92 |
55.0*
|
64.1 |
21.7% |
44.6% |
0% |
APASL 2016 |
78.0*/n.a./35.5 |
31 (33.7%)/7 (7.6%) |
AUC: |
Proportion at week 96 |
|
2Y: 0.81 |
High risk: 0% |
|
Intermediat: 2.4% |
|
Low risk: 14.3% |
Table 5.Proposed criteria to restart antiviral therapy after cessation of nucleos(t)ide analogues
Table 5.
|
Institution/Study, Site |
Retreatment criteria |
|
Criteria used in randomized controlled trials |
|
FINITE study, [102] Multicenter in Germany |
At least one of the criteria: |
|
· Increase of direct bilirubin by >1.5 mg/dL (>25 μmol/L) from baseline, and ALT >ULN |
|
· Increase in PT ≥2.0 s (INR ≥0.5) prolonged from baseline with adequate vitamin K therapy, and ALT >ULN |
|
· ALT >10X ULN with or without associated symptoms. |
|
· ALT >2X ULN and ≤5X ULN persisting for ≥84 days (12 weeks), and HBV DNA >20,000 copies/mL (equivalent to 357 IU/mL) |
|
· ALT >5X ULN and ≤10X ULN persisting for ≥28 days (4 weeks). |
|
Stop-NUC study, [103] Multicenter in Germany |
At least one of the criteria: |
|
· ALT >10X ULN |
|
· 10X ULN ≥ALT>5X ULN for ≥28 days |
|
· 5X ULN ≥ALT>2X ULN for ≥112 days and HBV DNA >2,000 IU/mL |
|
Increase of total bilirubin by >1.5X ULN |
|
Toronto-STOP study, [104] Toronto Centre for Liver Disease, Canada |
At least one of the criteria: |
|
· HBeAg seroreversion |
|
· HBV DNA >2,000 IU/mL and ALT >600 IU/mL at any visit |
|
· HBV DNA >2,000 IU/mL and ALT >200 IU/mL (5X ULN) on two consecutive visits |
|
· HBV DNA >2,000 IU/mL and ALT >200 IU/mL but <600 IU/mL for >6–8 weeks |
|
· HBV DNA >20,000 IU/mL on two consecutive visits at least 4 weeks apart. |
|
Criteria used in prospective observational study |
|
Queen Mary Hospital64, Hong Kong |
· Virological relapse: HBV DNA >2,000 IU/mL |
|
Australia multicenter study, [105] Australia |
At least one of the criteria: |
|
· HBV DNA >2,000 IU/mL and serum ALT >5X ULN for ≥16 weeks or ALT >10X ULN for ≥8 weeks |
|
· Clinical evidence of hepatic decompensation defined by INR ≥1.5 or bilirubin >2X ULN or ascites or hepatic encephalopathy Investigator discretion |
|
DARING-B study, [106] Laiko General Hospital and Hippokration General Hospital, Greece |
At least one of the criteria: |
|
· ALT >10X ULN |
|
· ALT >5X ULN and total bilirubin >2 mg/dL at the same visit |
|
· ALT >3X ULN and HBV DNA >100,000 IU/mL at the same visit |
|
· ALT >ULN and HBV DNA >2,000 IU/mL on three sequential visits. |
|
· According to patients’ and physicians’ decisions in case of virological relapse with HBV DNA >20,000 IU/mL |
|
Nanfang Hospital, [65,107] China |
Clinical relapse: HBV DNA >2,000 IU/mL and ALT >2X ULN |
|
Multiple centers in China [108] |
|
Taiwan National Health Insurance, [71] Taiwan |
ALT >2X ULN with 3 months apart and HBV DNA >2,000 IU/mL or total bilirubin >2 mg/dL, or prolongation of PT ≥3 seconds |
Table 6.Randomized controlled trial to assess cessation of nucleos(t)ide analogues in chronic hepatitis B patients
Table 6.
|
Study |
Scale/Region |
Primary outcome |
Key inclusion criteria |
Group |
Age/Caucasian/Male/Fibroscan (kPa) |
ETV or TDF (%)/Pre-Tx HBeAg (+)/HBsAg (log IU/mL)/NA duration (months) |
Clinical relapse, number (%) |
HBsAg loss, number (%) |
Adverse events, number (%) |
|
FINITE, Berg et al. [102] (2017) |
Multicenter/Germany |
HBsAg loss or seroconversion at week 144 |
TDF ≥4 years |
Stop: n=21 |
44.5†/18 (85.7%)/18 (85.7%)/6.1†
|
21 (100%)/0 (0%)/4.4†/n.a. |
At least 5 (23.8%)**,††
|
4 (19.0%) |
Grade 3/4: 5 (23.8%) |
|
HBV DNA <400 copies/mL ≥3.5 years |
|
Pre-Tx HBeAg(-) |
|
No advanced fibrosis/cirrhosis (by histology or Fibroscan) |
Continue: n=21 |
45.5†/19 (90.5%)/15 (71.4%)/5.0†
|
21 (100%)/0 (0%)/4.6†/n.a. |
1 (4.8%)**,††
|
0 (0%) |
Grade 3/4: 0 (0%) |
|
No history of decompensation |
|
Stop-NUC*, van Bömmel et al. [103] (2020) |
Multicenter/Germany |
HBsAg loss at week 96 |
NA ≥4 years |
Stop: n=79 |
51.6†/62 (78.5%)/50 (63.3%)/5.7†
|
71 (89.9%)/0 (0%)/3.5†/n.a. |
28 (35.4%)‡
|
10 (12.7%) |
n.a. |
|
HBV DNA <1,000 IU/mL ≥4 years |
|
Pre-Tx HBeAg(-) |
|
Pre-Tx HBV DNA >2,000 IU/mL |
|
No advanced fibrosis/cirrhosis (by histology of Fibroscan) |
Continue: n=79 |
52.0†/68 (82.2%)/51 (64.6%)/5.7†
|
72 (91.1%)/0 (0%)/3.6†/n.a. |
0 (0%)‡
|
0 (0%) |
n.a. |
|
Toronto-STOP, Liem et al. [104] (2019) |
Single center/Canada |
HBV DNA <2,000 IU/mL at week 48 |
NA ≥1 year |
Stop: n=45 |
59†/2%/26 (57.8%)/4.9†
|
45(100%)/27 (60.0%)/3.1†/72.0†
|
At least 10 (22.2%)§,∥
|
1 (0.2%)∥
|
22(48.9%): ALT >5X ULN |
|
Consolidation: |
1 (2.2%): bilirubin >66 μmol/L |
|
Pre-Tx:HBeAg(+): 1 year and HBeAb(+) |
|
Pre-Tx HBeAg(-): 3 years |
Continue: n=22 |
50†/5%/14 (63.6%)/5.2†
|
22 (100%)/13 (59.1%)/3.0†/61.2†
|
0 (0.0%)§,∥
|
1 (0.5%)∥
|
0 (0.0%) |
|
No cirrhosis (defined by histology or Fibroscan) |
Abbreviations
hepatitis B surface antigen
tenofovir disoproxil fumarate
covalently closed circular DNA
acute-on-chronic liver failure
Asian Pacific Association for the Study of the Liver
American Association for the Study of the Liver
European Association for the Study of the Liver
hepatitis B core-related antigen
Japan Society of Hepatology
REFERENCES
- 1. World Health Organization (WHO). Fact sheets/Detail/Hepatitis B. WHO web site, <https://www.who.int/news-room/fact-sheets/detail/hepatitis-b>. Accessed 16 Nov 2022.
- 2. Lok AS, McMahon BJ, Brown RS Jr, Wong JB, Ahmed AT, Farah W, et al. Antiviral therapy for chronic hepatitis B viral infection in adults: A systematic review and meta-analysis. Hepatology 2016;63:284-306.
- 3. Wu CY, Lin JT, Ho HJ, Su CW, Lee TY, Wang SY, et al. Association of nucleos(t)ide analogue therapy with reduced risk of hepatocellular carcinoma in patients with chronic hepatitis B: a nationwide cohort study. Gastroenterology 2014;147:143-151 e5.
- 4. Su TH, Hu TH, Chen CY, Huang YH, Chuang WL, Lin CC, et al.; C-TEAM study group and the Taiwan Liver Diseases Consortium. Four-year entecavir therapy reduces hepatocellular carcinoma, cirrhotic events and mortality in chronic hepatitis B patients. Liver Int 2016;36:1755-1764.
- 5. Liu Y, Corsa AC, Buti M, Cathcart AL, Flaherty JF, Miller MD, et al. No detectable resistance to tenofovir disoproxil fumarate in HBeAg+ and HBeAg-patients with chronic hepatitis B after 8 years of treatment. J Viral Hepat 2017;24:68-74.
- 6. Werle-Lapostolle B, Bowden S, Locarnini S, Wursthorn K, Petersen J, Lau G, et al. Persistence of cccDNA during the natural history of chronic hepatitis B and decline during adefovir dipivoxil therapy. Gastroenterology 2004;126:1750-1758.
- 7. Grudda T, Hwang HS, Taddese M, Quinn J, Sulkowski MS, Sterling RK, et al. Integrated hepatitis B virus DNA maintains surface antigen production during antiviral treatment. J Clin Invest 2022;132:e161818.
- 8. Seto WK, Hui AJ, Wong VW, Wong GL, Liu KS, Lai CL, et al. Treatment cessation of entecavir in Asian patients with hepatitis B e antigen negative chronic hepatitis B: a multicentre prospective study. Gut 2015;64:667-672.
- 9. Terrault NA, Lok ASF, McMahon BJ, Chang KM, Hwang JP, Jonas MM, et al. Update on prevention, diagnosis, and treatment of chronic hepatitis B: AASLD 2018 hepatitis B guidance. Hepatology 2018;67:1560-1599.
- 10. Sarin SK, Kumar M, Lau GK, Abbas Z, Chan HL, Chen CJ, et al. Asian-Pacific clinical practice guidelines on the management of hepatitis B: a 2015 update. Hepatol Int 2016;10:1-98.
- 11. European Association for the Study of the Liver. EASL 2017 Clinical Practice Guidelines on the management of hepatitis B virus infection. J Hepatol 2017;67:370-398.
- 12. Yip TC, Wong GL, Wong VW, Tse YK, Lui GC, Lam KL, et al. Durability of hepatitis B surface antigen seroclearance in untreated and nucleos(t)ide analogue-treated patients. J Hepatol 2018;68:63-72.
- 13. Hsu YC, Yeh ML, Wong GL, Chen CH, Peng CY, Buti M, et al. Incidences and determinants of functional cure during entecavir or tenofovir disoproxil fumarate for chronic hepatitis B. J Infect Dis 2021;224:1890-1899.
- 14. Jeng WJ, Chen YC, Chien RN, Sheen IS, Liaw YF. Incidence and predictors of hepatitis B surface antigen seroclearance after cessation of nucleos(t)ide analogue therapy in hepatitis B e antigen-negative chronic hepatitis B. Hepatology 2018;68:425-434.
- 15. Kim GA, Lim YS, An J, Lee D, Shim JH, Kim KM, et al. HBsAg seroclearance after nucleoside analogue therapy in patients with chronic hepatitis B: clinical outcomes and durability. Gut 2014;63:1325-1332.
- 16. Ford N, Scourse R, Lemoine M, Hutin Y, Bulterys M, Shubber Z, et al. Adherence to nucleos(t)ide analogue therapies for chronic hepatitis B infection: A systematic review and meta-analysis. Hepatol Commun 2018;2:1160-1167.
- 17. Madeddu G, Fiore V, Melis M, Ortu S, Mannu F, Muredda AA, et al. Mitochondrial toxicity and body shape changes during nucleos(t)ide analogues administration in patients with chronic hepatitis B. Sci Rep 2020;10:2014.
- 18. Liaw YF. Finite nucleos(t)ide analog therapy in HBeAg-negative chronic hepatitis B: an emerging paradigm shift. Hepatol Int 2019;13:665-673.
- 19. Hadziyannis SJ, Sevastianos V, Rapti I, Vassilopoulos D, Hadziyannis E. Sustained responses and loss of HBsAg in HBeAg-negative patients with chronic hepatitis B who stop long-term treatment with adefovir. Gastroenterology 2012;143:629-636.e1.
- 20. Lampertico P, Berg T. Less can be more: A finite treatment approach for HBeAg-negative chronic hepatitis B. Hepatology 2018;68:397-400.
- 21. Berg T, Lampertico P. The times they are a-changing - A refined proposal for finite HBV nucleos(t)ide analogue therapy. J Hepatol 2021;75:474-480.
- 22. Reijnders JG, Perquin MJ, Zhang N, Hansen BE, Janssen HL. Nucleos(t)ide analogues only induce temporary hepatitis B e antigen seroconversion in most patients with chronic hepatitis B. Gastroenterology 2010;139:491-498.
- 23. Tseng TC, Liu CJ, Su TH, Yang HC, Wang CC, Chen CL, et al. Young chronic hepatitis B patients with nucleos(t)ide analogue-induced hepatitis B e antigen seroconversion have a higher risk of HBV reactivation. J Infect Dis 2012;206:1521-1531.
- 24. World Health Organization. Guidelines for the prevention, care and treatment of persons with chronic hepatitis B infection. Geneva: World Health Organization; 2015.
- 25. Coffin CS, Fung SK, Alvarez F, Cooper CL, Doucette KE, Fournier C, et al. Management of hepatitis B virus infection: 2018 Guidelines from the Canadian Association for the Study of Liver Disease and Association of Medical Microbiology and Infectious Disease Canada. Can Liver J 2018;1:156-217.
- 26. Wang G, Duan Z. Guidelines for prevention and treatment of chronic hepatitis B. J Clin Transl Hepatol 2021;9:769-791.
- 27. Drafting Committee for Hepatitis Management Guidelines, the Japan Society of Hepatology. Japan Society of Hepatology Guidelines for the Management of Hepatitis B Virus Infection: 2019 update. Hepatol Res 2020;50:892-923.
- 28. Korean Association for the Study of the Liver (KASL). KASL clinical practice guidelines for management of chronic hepatitis B. Clin Mol Hepatol 2022;28:276-331. Erratum in: Clin Mol Hepatol 2022;28:940.
- 29. Westin J, Aleman S, Castedal M, Duberg AS, Eilard A, Fischler B, et al. Management of hepatitis B virus infection, updated Swedish guidelines. Infect Dis (Lond) 2020;52:1-22.
- 30. Tabak F, Yurdaydın C, Kaymakoğlu S, Akarsu M, Akıncı EG, Akkız H, et al. Diagnosis, management and treatment of hepatitis B virus infection: Turkey 2017 Clinical Practice Guidelines. Turk J Gastroenterol 2017;28(Suppl 2):73-83.
- 31. Van Hees S, Bourgeois S, Van Vlierberghe H, Sersté T, Francque S, Michielsen P, et al.; Belgian NA Stop Study Group. Stopping nucleos(t)ide analogue treatment in Caucasian hepatitis B patients after HBeAg seroconversion is associated with high relapse rates and fatal outcomes. Aliment Pharmacol Ther 2018;47:1170-1180.
- 32. Hall SAL, Vogrin S, Wawryk O, Burns GS, Visvanathan K, Sundararajan V, et al. Discontinuation of nucleot(s)ide analogue therapy in HBeAg-negative chronic hepatitis B: a meta-analysis. Gut 2022;71:1629-1641.
- 33. Hirode G, Hansen BE, Chen CH, Su TH, Wong G, Seto WK, et al.; RETRACT-B study group. Incidence of hepatic decompensation after nucleos(t)ide analog withdrawal: Results from a large, international, multiethnic cohort of patients with chronic hepatitis B (RETRACT-B Study). Am J Gastroenterol 2023 Mar 14;doi: 10.14309/ajg.0000000000002203.
- 34. Hsu YC, Wu JL, Tseng CH, Nguyen MH, Lin CW, Hung CL. Severe acute exacerbation after cessation of nucleos(t)ide analog for chronic hepatitis B: A real-world study of routine practice. Clin Gastroenterol Hepatol 2022;20:1413-1415.e3.
- 35. Liu YC, Jeng WJ, Peng CW, Chien RN, Liaw YF. Off-tenofovir hepatitis flares in HBeAg-negative patients occur earlier, more frequent and severe than those off-entecavir therapies. Liver Int 2022;42:551-560.
- 36. Chang ML, Liaw YF. Hepatitis B flares in chronic hepatitis B: pathogenesis, natural course, and management. J Hepatol 2014;61:1407-1417.
- 37. Ghany MG, Feld JJ, Chang KM, Chan HLY, Lok ASF, Visvanathan K, et al. Serum alanine aminotransferase flares in chronic hepatitis B infection: the good and the bad. Lancet Gastroenterol Hepatol 2020;5:406-417.
- 38. Perrillo RP. Acute flares in chronic hepatitis B: the natural and unnatural history of an immunologically mediated liver disease. Gastroenterology 2001;120:1009-1022.
- 39. Paul S, Saxena A, Terrin N, Viveiros K, Balk EM, Wong JB. Hepatitis B virus reactivation and prophylaxis during solid tumor chemotherapy: A systematic review and meta-analysis. Ann Intern Med 2016;164:30-40.
- 40. Pauly MP, Tucker LY, Szpakowski JL, Ready JB, Baer D, Hwang J, et al. Incidence of hepatitis B virus reactivation and hepatotoxicity in patients receiving long-term treatment with tumor necrosis factor antagonists. Clin Gastroenterol Hepatol 2018;16:1964-1973 e1.
- 41. Hsu YC, Lin YH, Lee TY, Nguyen MH, Ho HJ, Kao FY, et al. Severe hepatitis flare and related mortality after discontinuation of oral antiviral treatment in patients with chronic hepatitis b: A population-based study. Hepatology 2021;74:18A.
- 42. Hsu YC, Tseng CH, Su TH, Kao JH, Nguyen MH. Pooling data to assess risks and benefits of discontinuing nucleos(t)ide analogs in patients with chronic hepatitis B: challenges and opportunities. Gut 2022;71:1238-1240.
- 43. Tseng CH, Chen TH, Wu JL, Lee TY, Borghi JA, Lin JT, et al. Serious adverse events after cessation of nucleos(t)ide analogues in individuals with chronic hepatitis B: A systematic review and meta-analysis. JHEP Rep 2022;5:100617.
- 44. Ma TL, Hu TH, Hung CH, Wang JH, Lu SN, Chen CH. Incidence and predictors of retreatment in chronic hepatitis B patients after discontinuation of entecavir or tenofovir treatment. PLoS One 2019;14:e0222221.
- 45. Sonneveld MJ, Park JY, Kaewdech A, Seto WK, Tanaka Y, Carey I, et al.; CREATE Study Group. Prediction of sustained response after nucleo(s)tide analogue cessation using HBsAg and HBcrAg levels: A multicenter study (CREATE). Clin Gastroenterol Hepatol 2022;20:e784-e793.
- 46. Wong GL, Chan HL, Yuen BW, Tse YK, Luk HW, Yip TC, et al. The safety of stopping nucleos(t)ide analogue treatment in patients with HBeAg-negative chronic hepatitis B. Liver Int 2020;40:549-557.
- 47. Lai CY, Yang SS, Lee SW, Tsai HJ, Lee TY. Cessation of nucleos(t) ide analogue therapy in non-Cirrhotic hepatitis B patients with prior severe acute exacerbation. J Clin Med 2021;10:4883.
- 48. Hirode G, Choi HSJ, Chen CH, Su TH, Seto WK, Van Hees S, et al.; RETRACT-B Study Group. Off-therapy response after nucleos(t) ide analogue withdrawal in patients with chronic hepatitis B: An international, multicenter, multiethnic cohort (RETRACT-B study). Gastroenterology 2022;162:757-771 e4.
- 49. Liaw YF, Kao JH, Piratvisuth T, Chan HL, Chien RN, Liu CJ, et al. Asian-Pacific consensus statement on the management of chronic hepatitis B: a 2012 update. Hepatol Int 2012;6:531-561. Erratum in: Hepatol Int 2012;6:809-810.
- 50. Höner Zu Siederdissen C, Rinker F, Maasoumy B, Wiegand SB, Filmann N, et al. Viral and host responses after stopping long-term nucleos(t)ide analogue therapy in HBeAg-negative chronic hepatitis B. J Infect Dis 2016;214:1492-1497.
- 51. Rinker F, Zimmer CL, Höner Zu Siederdissen C, Manns MP, Kraft ARM, et al. Hepatitis B virus-specific T cell responses after stopping nucleos(t)ide analogue therapy in HBeAg-negative chronic hepatitis B. J Hepatol 2018;69:584-593.
- 52. van Bömmel F, Berg T. Risks and benefits of discontinuation of nucleos(t)ide analogue treatment: A Treatment concept for patients with HBeAg-negative chronic hepatitis B. Hepatol Commun 2021;5:1632-1648.
- 53. Kao JH, Berg T. Nucleos(t)ide analogues in patients with chronic hepatitis B: to stop or not to stop? Gut 2019;68:2105-2106.
- 54. Hsu YC, Mo LR, Chang CY, Wu MS, Kao JH, Wang WL, et al. Association between serum level of hepatitis B surface antigen at end of entecavir therapy and risk of relapse in E antigen-negative patients. Clin Gastroenterol Hepatol 2016;14:1490-1498.e3.
- 55. Chen CH, Hung CH, Hu TH, Wang JH, Lu SN, Su PF, et al. Association between level of hepatitis B surface antigen and relapse after entecavir therapy for chronic hepatitis B virus infection. Clin Gastroenterol Hepatol 2015;13:1984-1992.e1.
- 56. Chen CH, Lu SN, Hung CH, Wang JH, Hu TH, Changchien CS, et al. The role of hepatitis B surface antigen quantification in predicting HBsAg loss and HBV relapse after discontinuation of lamivudine treatment. J Hepatol 2014;61:515-522.
- 57. Wang CC, Tseng KC, Hsieh TY, Tseng TC, Lin HH, Kao JH. Assessing the durability of entecavir-treated hepatitis B using quantitative HBsAg. Am J Gastroenterol 2016;111:1286-1294.
- 58. Liu J, Li T, Zhang L, Xu A. The role of hepatitis B surface antigen in nucleos(t)ide analogues cessation among Asian patients with chronic hepatitis B: A systematic review. Hepatology 2019;70:1045-1055.
- 59. Tseng TN, Hu TH, Wang JH, Kuo YH, Hung CH, Lu SN, et al. Incidence and factors associated with HBV relapse after cessation of entecavir or tenofovir in patients with HBsAg below 100 IU/mL. Clin Gastroenterol Hepatol 2020;18:2803-2812.e2.
- 60. Maasoumy B, Wiegand SB, Jaroszewicz J, Bremer B, Lehmann P, Deterding K, et al. Hepatitis B core-related antigen (HBcrAg) levels in the natural history of hepatitis B virus infection in a large European cohort predominantly infected with genotypes A and D. Clin Microbiol Infect 2015;21:606.e1-10.
- 61. Chen EQ, Feng S, Wang ML, Liang LB, Zhou LY, Du LY, et al. Serum hepatitis B core-related antigen is a satisfactory surrogate marker of intrahepatic covalently closed circular DNA in chronic hepatitis B. Sci Rep 2017;7:173.
- 62. Hsu YC, Nguyen MH, Mo LR, Wu MS, Yang TH, Chen CC, et al. Combining hepatitis B core-related and surface antigens at end of nucleos(t)ide analogue treatment to predict off-therapy relapse risk. Aliment Pharmacol Ther 2019;49:107-115.
- 63. Huang PY, Wang JH, Hung CH, Lu SN, Hu TH, Chen CH. The role of hepatitis B virus core-related antigen in predicting hepatitis B virus relapse after cessation of entecavir in hepatitis B e antigen-negative patients. J Viral Hepat 2021;28:1141-1149.
- 64. Seto WK, Liu KS, Mak LY, Cloherty G, Wong DK, Gersch J, et al. Role of serum HBV RNA and hepatitis B surface antigen levels in identifying Asian patients with chronic hepatitis B suitable for entecavir cessation. Gut 2021;70:775-783.
- 65. Liao G, Ding X, Xia M, Wu Y, Chen H, Fan R, et al. Hepatitis B core-related antigen is a biomarker for off-treatment relapse after long-term nucleos(t)ide analog therapy in patients with chronic hepatitis B. Int J Gen Med 2021;14:4967-4976.
- 66. Papatheodoridi M, Hadziyannis E, Berby F, Zachou K, Testoni B, Rigopoulou E, et al. Predictors of hepatitis B surface antigen loss, relapse and retreatment after discontinuation of effective oral antiviral therapy in noncirrhotic HBeAg-negative chronic hepatitis B. J Viral Hepat 2020;27:118-126.
- 67. Jeng WJ, Sheen IS, Chen YC, Hsu CW, Chien RN, Chu CM, et al. Off-therapy durability of response to entecavir therapy in hepatitis B e antigen-negative chronic hepatitis B patients. Hepatology 2013;58:1888-1896.
- 68. Kuo MT, Hu TH, Hung CH, Wang JH, Lu SN, Tsai KL, et al. Hepatitis B virus relapse rates in chronic hepatitis B patients who discontinue either entecavir or tenofovir. Aliment Pharmacol Ther 2019;49:218-228.
- 69. Chiu SM, Kuo YH, Wang JH, Hung CH, Hu TH, Lu SN, et al. Associations of HBV genotype B vs C infection with relapse after cessation of entecavir or tenofovir therapy. Clin Gastroenterol Hepatol 2020;18:2989-2997.e3.
- 70. Cheng HR, Yang HC, Lin SR, Yang TY, Lin YY, Su TH, et al. Combined viral quasispecies diversity and hepatitis B core-related antigen predict off-nucleos(t)ide analog durability in HBeAg-negative patients. Hepatol Int 2021;15:582-592.
- 71. Su TH, Yang HC, Tseng TC, Liou JM, Liu CH, Chen CL, et al. Distinct relapse rates and risk predictors after discontinuing tenofovir and entecavir therapy. J Infect Dis 2018;217:1193-1201.
- 72. Tseng CH, Hsu YC, Chang CY, Tseng TC, Wu MS, Lin JT, et al. Quantification of serum hepatitis B core antibody to predict off-entecavir relapse in patients with chronic hepatitis B. J Formos Med Assoc 2018;117:915-921.
- 73. Chi H, Li Z, Hansen BE, Yu T, Zhang X, Sun J, et al. Serum level of antibodies against hepatitis B core protein is associated with clinical relapse after discontinuation of nucleos(t)ide analogue therapy. Clin Gastroenterol Hepatol 2019;17:182-191.e1.
- 74. Kranidioti H, Manolakopoulos S, Kontos G, Breen MS, Kourikou A, Deutsch M, et al. Immunological biomarkers as indicators for outcome after discontinuation of nucleos(t)ide analogue therapy in patients with HBeAg-negative chronic hepatitis B. J Viral Hepat 2019;26:697-709.
- 75. Sonneveld MJ, Chiu SM, Park JY, Brakenhoff SM, Kaewdech A, Seto WK, et al.; CREATE study group. Probability of HBsAg loss after nucleo(s)tide analogue withdrawal depends on HBV genotype and viral antigen levels. J Hepatol 2022;76:1042-1050.
- 76. Tong S, Revill P. Overview of hepatitis B viral replication and genetic variability. J Hepatol 2016;64(1 Suppl):S4-S16.
- 77. Maini MK, Boni C, Ogg GS, King AS, Reignat S, Lee CK, et al. Direct ex vivo analysis of hepatitis B virus-specific CD8(+) T cells associated with the control of infection. Gastroenterology 1999;117:1386-1396.
- 78. Maini MK, Boni C, Lee CK, Larrubia JR, Reignat S, Ogg GS, et al. The role of virus-specific CD8(+) cells in liver damage and viral control during persistent hepatitis B virus infection. J Exp Med 2000;191:1269-1280.
- 79. Iannacone M, Guidotti LG. Immunobiology and pathogenesis of hepatitis B virus infection. Nat Rev Immunol 2022;22:19-32.
- 80. Rivino L, Le Bert N, Gill US, Kunasegaran K, Cheng Y, Tan DZ, et al. Hepatitis B virus-specific T cells associate with viral control upon nucleos(t)ide-analogue therapy discontinuation. J Clin Invest 2018;128:668-681.
- 81. García-López M, Lens S, Pallett LJ, Testoni B, Rodríguez-Tajes S, Mariño Z, et al. Viral and immune factors associated with successful treatment withdrawal in HBeAg-negative chronic hepatitis B patients. J Hepatol 2021;74:1064-1074.
- 82. Boni C, Fisicaro P, Valdatta C, Amadei B, Di Vincenzo P, Giuberti T, et al. Characterization of hepatitis B virus (HBV)-specific T-cell dysfunction in chronic HBV infection. J Virol 2007;81:4215-4225.
- 83. Peña-Asensio J, Calvo H, Miquel J, Sanz-de-Villalobos E, González-Praetorius A, Torralba M, et al. Model to predict ontreatment restoration of functional HBV-specific CD8+ cell response foresees off-treatment HBV control in eAg-negative chronic hepatitis B. Aliment Pharmacol Ther 2022;55:1545-1559.
- 84. Ito K, Tanaka Y, Orito E, Hirashima N, Ide T, Hino T, et al. Predicting relapse after cessation of Lamivudine monotherapy for chronic hepatitis B virus infection. Clin Infect Dis 2004;38:490-495.
- 85. Chi H, Hansen BE, Yim C, Arends P, Abu-Amara M, van der Eijk AA, et al. Reduced risk of relapse after long-term nucleos(t) ide analogue consolidation therapy for chronic hepatitis B. Aliment Pharmacol Ther 2015;41:867-876.
- 86. Jeng WJ, Chen YC, Sheen IS, Lin CL, Hu TH, Chien RN, et al. Clinical relapse after cessation of tenofovir therapy in hepatitis B e antigen-negative patients. Clin Gastroenterol Hepatol 2016;14:1813-1820.e1.
- 87. Papatheodoridis G, Vlachogiannakos I, Cholongitas E, Wursthorn K, Thomadakis C, Touloumi G, et al. Discontinuation of oral antivirals in chronic hepatitis B: A systematic review. Hepatology 2016;63:1481-1492.
- 88. Choi HSJ, Hirode G, Chen CH, Su TH, Seto WK, Van Hees S, et al.; RETRACT-B study group. Differential relapse patterns after discontinuation of entecavir vs tenofovir disoproxil fumarate in chronic hepatitis B. Clin Gastroenterol Hepatol 2022 Jul 19;doi: 10.1016/j.cgh.2022.07.005.
- 89. Höner Zu Siederdissen C, Hui AJ, Sukeepaisarnjaroen W, Tangkijvanich P, Su WW, et al. Contrasting timing of virological relapse after discontinuation of tenofovir or entecavir in hepatitis B e Antigen-negative patients. J Infect Dis 2018;218:1480-1484.
- 90. Drafting Committee for Hepatitis Management Guidelines and the Japan Society of Hepatology. JSH Guidelines for the Management of Hepatitis B Virus Infection. Hepatol Res 2014;44 Suppl S1:1-58.
- 91. Kaewdech A, Assawasuwannakit S, Sripongpun P, Chamroonkul N, Tangkijvanich P, Piratvisuth T. Clinical utility of SCALE-B to predict hepatitis B virus relapse, hepatitis B surface antigen loss after antiviral cessation in Asian patients after 2-year follow-up. Front Med (Lausanne) 2022;9:859430.
- 92. Kao JH, Jeng WJ, Ning Q, Su TH, Tseng TC, Ueno Y, et al. APASL guidance on stopping nucleos(t)ide analogues in chronic hepatitis B patients. Hepatol Int 2021;15:833-851.
- 93. Chen CH, Jeng WJ, Hu TH, Liu YC, Wang JH, Hung CH, et al. HBV relapse rates in patients who discontinue tenofovir disoproxil fumarate with or without switching to tenofovir alafenamide. Dig Liver Dis 2023 Feb 1;doi: 10.1016/j.dld.2023.01.154.
- 94. Liem KS, Chi H, Fung S, Wong DK, Yim C, Noureldin S, et al. Early virologic relapse predicts alanine aminotransferase flares after nucleos(t)ide analogue withdrawal in patients with chronic hepatitis B. J Viral Hepat 2022;29:986-993.
- 95. Hsu YC, Mo LR, Chang CY, Wu MS, Yang TH, Kao JH, et al. Serum viral load at the virological relapse predicts subsequent clinical flares in chronic hepatitis B patients off entecavir therapy. J Gastroenterol Hepatol 2017;32:1512-1519.
- 96. Liu YC, Jeng WJ, Peng CW, Chien RN, Liaw YF. The role of offtherapy viral kinetics in the timing and severity of flares in hepatitis B e antigen-negative patients. Clin Gastroenterol Hepatol 2022 Aug 28;doi: 10.1016/j.cgh.2022.08.021.
- 97. Chien NH, Huang YT, Wu CY, Chang CY, Wu MS, Kao JH, et al. Time-varying serum gradient of hepatitis B surface antigen predicts risk of relapses after off-NA therapy. BMC Gastroenterol 2017;17:154.
- 98. Chu CM. Natural history of chronic hepatitis B virus infection in adults with emphasis on the occurrence of cirrhosis and hepatocellular carcinoma. J Gastroenterol Hepatol 2000;15 Suppl:E25-30.
- 99. Chen CJ, Yang HI, Su J, Jen CL, You SL, Lu SN, et al.; REVEAL-HBV Study Group. Risk of hepatocellular carcinoma across a biological gradient of serum hepatitis B virus DNA level. JAMA 2006;295:65-73.
- 100. Yang HI, Yuen MF, Chan HL, Han KH, Chen PJ, Kim DY, et al.; REACH-B Working Group. Risk estimation for hepatocellular carcinoma in chronic hepatitis B (REACH-B): development and validation of a predictive score. Lancet Oncol 2011;12:568-574.
- 101. Hsu YC, Tseng CH, Huang YT, Yang HI. Application of risk scores for hepatocellular carcinoma in patients with chronic hepatitis B: Current status and future perspective. Semin Liver Dis 2021;41:285-297.
- 102. Berg T, Simon KG, Mauss S, Schott E, Heyne R, Klass DM, et al. Long-term response after stopping tenofovir disoproxil fumarate in non-cirrhotic HBeAg-negative patients - FINITE study. J Hepatol 2017;67:918-924.
- 103. van Bömmel F, Stein K, Heyne R, Möller H, Petersen J, Buggisch P, et al. Response to discontinuation of long-term nucleos(t)ide analogue treatment in HBeAg negative patients: Results of the Stop-NUC trial. J Hepatol 2020;73:S118-S119.
- 104. Liem KS, Fung S, Wong DK, Yim C, Noureldin S, Chen J, et al. Limited sustained response after stopping nucleos(t)ide analogues in patients with chronic hepatitis B: results from a randomised controlled trial (Toronto STOP study). Gut 2019;68:2206-2213.
- 105. Hall SAL, Burns GS, Anagnostou D, Vogrin S, Sundararajan V, Ratnam D, et al. Stopping nucleot(s)ide analogues in noncirrhotic HBeAg-negative chronic hepatitis B patients: HBsAg loss at 96weeks is associated with low baseline HBsAg levels. Aliment Pharmacol Ther 2022;56:310-320.
- 106. Papatheodoridis GV, Rigopoulou EI, Papatheodoridi M, Zachou K, Xourafas V, Gatselis N, et al. DARING-B: discontinuation of effective entecavir or tenofovir disoproxil fumarate long-term therapy before HBsAg loss in non-cirrhotic HBeAg-negative chronic hepatitis B. Antivir Ther 2018;23:677-685. Erratum in: Antivir Ther 2018;23:711.
- 107. Xia M, Chi H, Wu Y, Hansen BE, Li Z, Liu S, et al. Serum hepatitis B virus RNA level is associated with biochemical relapse in patients with chronic hepatitis B infection who discontinue nucleos(t)ide analogue treatment. Aliment Pharmacol Ther 2021;54:709-714.
- 108. Xie Y, Li M, Ou X, Zheng S, Gao Y, Xu X, et al. HBeAg-positive patients with HBsAg <100 IU/mL and negative HBV RNA have lower risk of virological relapse after nucleos(t)ide analogues cessation. J Gastroenterol 2021;56:856-867.
- 109. Hsu YC, Wu CY, Chang CY, Tai CM, Tseng CH, Perng DS, et al. Pretreatment viral DNA stratifies mortality risk in patients receiving antiviral therapy for severe acute exacerbation of chronic hepatitis B. Antivir Ther 2013;18:221-228.
- 110. Chen CH, Lin CL, Hu TH, Hung CH, Tseng PL, Wang JH, et al. Entecavir vs. lamivudine in chronic hepatitis B patients with severe acute exacerbation and hepatic decompensation. J Hepatol 2014;60:1127-1134.
- 111. Liaw YF, Jeng WJ, Chang ML. HBsAg kinetics in retreatment decision for off-therapy hepatitis B Flare in HBeAg-negative patients. Gastroenterology 2018;154:2280-2281.
- 112. Chien RN, Liaw YF. Re-treatment for severe hepatitis flare in HBeAg-negative chronic hepatitis B: An appraisal with combined HBsAg/ALT kinetics. J Viral Hepat 2020;27:544-547.
- 113. McDonald CJ. Medical heuristics: the silent adjudicators of clinical practice. Ann Intern Med 1996;124(1 Pt 1):56-62.
- 114. Papatheodoridis GV, Manolakopoulos S, Su TH, Siakavellas S, Liu CJ, Kourikou A, et al. Significance of definitions of relapse after discontinuation of oral antivirals in HBeAg-negative chronic hepatitis B. Hepatology 2018;68:415-424.
- 115. Guyatt GH, Oxman AD, Vist G, Kunz R, Brozek J, Alonso-Coello P, et al. GRADE guidelines: 4. Rating the quality of evidence--study limitations (risk of bias). J Clin Epidemiol 2011;64:407-415.
- 116. Gerstein HC, McMurray J, Holman RR. Real-world studies no substitute for RCTs in establishing efficacy. Lancet 2019;393:210-211.
- 117. Agarwal K, Lok J, Carey I, Shivkar Y, Biermer M, Berg T, et al. A case of HBV-induced liver failure in the REEF-2 phase II trial: Implications for finite treatment strategies in HBV ‘cure’. J Hepatol 2022;77:245-248.


